Rounding and heaping of weight
Recorded weight is a mixture of 3 rounding modes (whole_kg, scale_0.1, scale_0.05); the model gives the true value's distribution for each record.
| Date | 2026-10-13 |
| Status | current |
| Methods | Rounding, heaping and value resolution |
| Variables | Weight |
Background
- Weight is mostly a mix of two scale resolutions rather than human rounding.
- About 30% of weights come from a scale that reads to 0.05 kg and the rest from one that reads to 0.1 kg; about 3% are whole kilograms written in.
Data
- 6,388 values, none missing or zero; 5 values finer than 0.05 kg are flagged off-grid.
- Fitted to adults, first case per patient (6,041). 137 of 237 repeat patients have the same weight in every case.
- 57 children get native resolution (flag
child_native_resolution).
Method
- Digits were screened at the finest observed resolution (two decimals).
- Latent: log-t regression on sex and age (quadratic). The Student-t was compared with a log-normal.
- Each device resolution is a mode, and its share may depend on department.
- Tested: department effect on the scale share, a half-kilogram mode, and an emergency effect on whole kilograms.
Results
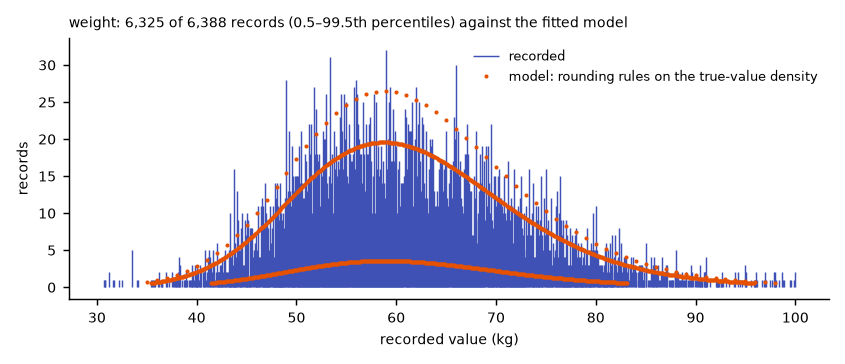
- Median latent weight is 58.3 kg for a woman aged 40 and 68.2 kg for a man, about 8% lower at 75.
- The Student-t beats the log-normal by 66 BIC points.
- A department effect on the scale share improves BIC (77,941 to 77,930). The finer scale seems to be used mainly on general surgery wards.
- A half-kilogram mode and an emergency effect on whole kilograms did not help.
- The expected share of each two-decimal ending matches the data, and the engine reproduces the log-likelihood (−38,917.2 against −38,917.3).
Discussion
- The first screen suggested a 0.2 kg scale, because even tenths looked more common. That was an artefact: rounding .x5 values to one decimal sends them to the even neighbour. At two decimals there is no even-digit excess, and the hypothesis was dropped.
- The lesson went into the checklist: screen digits at the finest observed resolution only, never after rounding.
- Measured weights get SD 0.5% of body weight (Khosla & Billewicz 1964); inpatients weighed at the same time each day vary by 0.4 kg or less (Vivanti et al. 2013).
- Written-in weights are treated as self-reported: under-reported by 0.55 kg in men and 0.67 kg in women, SD about 2.7 kg (2018 Korea Community Health Survey).
- The API needs sex, age and department.
Limitations
- Clothing is not included in the measurement variability.
- Measurement variability comes from the literature, not from this dataset.
Model
Model file: …/models/weight.model.json. Read from the pinned snapshot of vitaldb-resolution at commit bb03ddfc8a (2026-10-18).
How a true value becomes the recorded one. The rules are tried in order: a record not taken by an earlier rule is taken by this one with the probability shown (where its condition holds); the last rule takes the rest. Shares of all records depend on the conditions and the true value, so the model must be evaluated for them; the probabilities below are the fitted ones.
| Order | Rule | Rounds to | Probability if reached | Applies when |
|---|---|---|---|---|
| 1 | whole_kg | 1 kg (nearest) | 2.9 % | always |
| 2 | scale_0.1 | 0.1 kg (nearest) | 66.0 % | varies with department |
| 3 | scale_0.05 | 0.05 kg (nearest) | the rest | always |
| Recorded resolution | 0.05 |
| True-value density | log_student_t_regression |
| Covariates | sex, age, department |
| Fitted on | 6,041 records (clinical_data.csv) |
| BIC | 77,930 |
| Fitted | 2026-10-13 |
- Two scale resolutions are present (0.05 and 0.1 kg); modelled as modes rather than overridden.
- Measurement variability (beyond rounding): SD 0.5% of the value; for written-in values, SD 2.7 kg (from literature, not fitted).
Sources the model cites:
- Khosla T, Billewicz WZ. Measurement of change in body-weight. Br J Nutr. 1964;18(1):227-239. doi:10.1079/BJN19640022
- Vivanti A, Yu L, Palmer M, Dakin L, Sun J, Campbell K. Short-term body weight fluctuations in older well-hydrated hospitalised patients. J Hum Nutr Diet. 2013;26(5):429-435. doi:10.1111/jhn.12034
- Ko Y, Choi S, Won J, Lee YK, Kim DH, Lee SK. Differences in accuracy of height, weight, and body mass index between self-reported and measured using the 2018 Korea Community Health Survey data. Epidemiol Health. 2022;44:e2022024. doi:10.4178/epih.e2022024
Worked examples
| Example | Side | Status | Summary |
|---|---|---|---|
| A regression that carries rounding uncertainty through | value | draft | Acute kidney injury after surgery against intraoperative urine output (mL/kg/h), fitted once on the recorded numbers and once per draw from the true-value distributions: the rounding moves 14% of cases across the oliguria threshold, but widens the confidence interval of the cohort's regression by at most 4%. |
| Oliguria labels for a prediction model | value | draft | One label per patient, oliguric or not, from three rounded numbers: 10% of labels are uncertain and 2.6% are expected to be wrong, which sets a floor under the error any model can be measured to have. A typical model is barely affected; a good one is. |
| Urine output in mL/kg/h as a distribution | value | draft | Intraoperative urine output per kilogram per hour, from three rounded inputs, as a probability distribution per case: one case in ten cannot be placed confidently on either side of 0.5 mL/kg/h. |
Code
References
- Khosla T, Billewicz WZ. Measurement of change in body-weight. Br J Nutr. 1964;18(1):227-239. ↗
- Vivanti A, Yu L, Palmer M, Dakin L, Sun J, Campbell K. Short-term body weight fluctuations in older well-hydrated hospitalised patients. J Hum Nutr Diet. 2013;26(5):429-435. ↗
Tags: generated, vitaldb-resolution